3. TB-4 Benefits (Research-Supported)
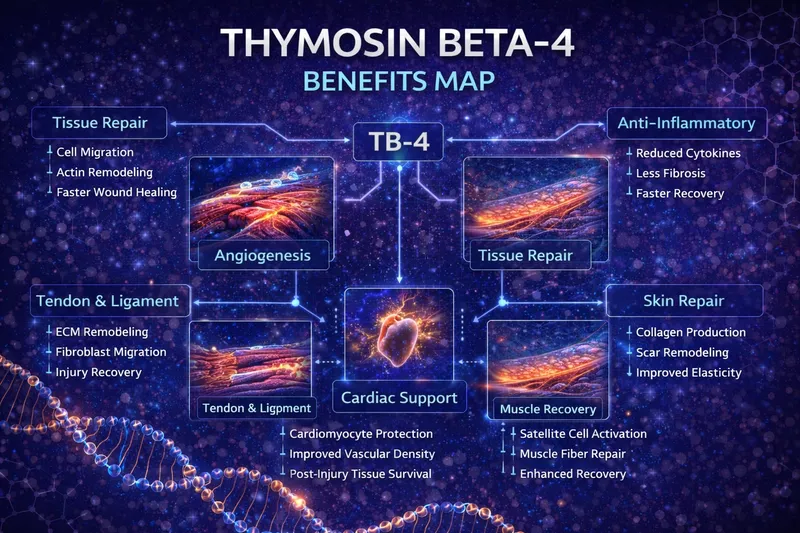
Each benefit below is backed by published research-model data. We've linked the primary sources so you can verify every claim.
Benefit #1 — Tissue Repair & Regeneration
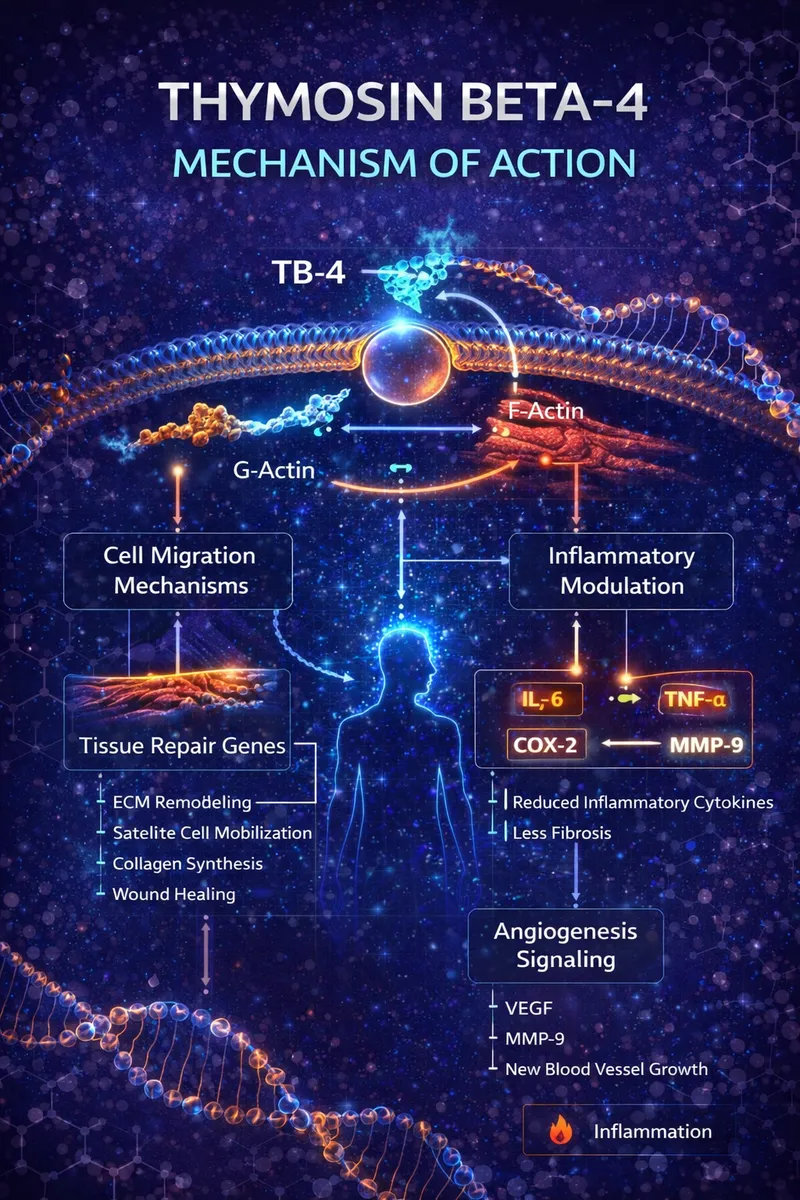
TB-4 is one of the strongest cell-migration agents studied in animal models. It enables damaged tissue to rebuild faster through three coordinated mechanisms:
- Actin polymerization — creates the structural scaffold for new tissue formation
- Cell migration — chemotactically recruits cells into injured areas
- Matrix remodeling — promotes organized collagen deposition for healthier ECM after injury
A landmark 1999 study by Malinda et al. demonstrated that TB-4 applied topically or intraperitoneally significantly increased re-epithelialization, collagen deposition, and angiogenesis in full-thickness wound models (Malinda et al., 1999). Follow-up research showed treated wounds healed with minimal scarring and without loss of wound breaking strength — with visibly superior organized collagen fibers under polarized light microscopy (Ehrlich & Hazard, 2010).
A comprehensive review of animal models confirmed consistent findings: faster wound closure, reduced tissue necrosis, and improved structural remodeling across dermal, corneal, and cardiac tissues (Philp & Kleinman, 2010).
Clinical translation — RGN-259: TB-4's wound healing properties have reached human clinical trials through RGN-259, a 0.1% thymosin beta-4 ophthalmic solution developed by RegeneRx. In a Phase III randomized, placebo-controlled trial in neurotrophic keratopathy, persistent corneal epithelial defects completely healed after 4 weeks in 6 of 10 RGN-259 patients versus 1 of 8 on placebo (p = 0.0656, a trend), with improved ocular comfort and no significant adverse effects reported (Sosne et al., 2022). An earlier small Phase 2 trial in severe dry eye reported a 35.1% reduction in ocular discomfort and a 59.1% reduction in corneal staining versus vehicle at day 56 (Sosne et al., 2015). RGN-259 represents the most advanced clinical application of TB-4 to date and validates the peptide's tissue repair mechanisms in human patients.
Benefit #2 — Angiogenesis (New Blood Vessel Growth)
One of TB-4's most clinically relevant effects is its role in angiogenesis — the formation of new blood vessels from existing vasculature.
In human umbilical vein endothelial cells, TB-4 induced angiogenic tube formation through the Notch signaling pathway, an effect blocked by Notch1/Notch4 knockdown (Lv et al., 2013). The actin-binding domain directly promotes endothelial cell migration, adhesion, tubule formation, and aortic ring sprouting (Smart et al., 2007).
This matters for:
- Wound healing — new vessels deliver oxygen and nutrients to damaged tissue
- Tendon and ligament recovery — tendons are notoriously avascular; angiogenesis accelerates repair
- Post-injury tissue survival — rescued blood supply prevents secondary necrosis
- Cardiac repair — the reason TB-4 is studied in myocardial infarction models
TB-4 is so active in angiogenesis that it was developed for clinical evaluation in ischemic heart disease, where restoring blood flow to damaged myocardium is critical (Crockford, 2007).
Benefit #3 — Anti-Inflammatory & Anti-Fibrotic Effects
TB-4 reduces key inflammatory markers in research models and simultaneously downregulates fibrosis pathways — a dual effect that's difficult to achieve with single compounds.
On the inflammatory side, TB-4 suppresses TNF-α-induced NF-κB activation, reducing downstream production of proinflammatory cytokines and chemokines (Qiu et al., 2011). A 2018 review described TB-4 resolving inflammation by restoring autophagy, suggesting therapeutic potential for inflammatory diseases with defective autophagy (Renga et al., 2018).
On the anti-fibrotic side, TB-4 prevents pathological scarring by switching the wound healing response from fibrotic to regenerative. A 2022 review described this as the "anti-fibrotic switch" — TB-4 modulates the balance between tissue repair and excessive scar formation (Goldstein & Kleinman, 2022). In a mouse model of ethanol- and LPS-induced liver injury, TB-4 prevented oxidative stress and inflammation and downregulated fibrogenic genes including collagen 1 and α-smooth muscle actin (Shah et al., 2018).
The practical result:
- Less scar tissue at injury sites
- Improved soft-tissue recovery with better functional outcomes
- Reduced pathological fibrosis in organ injury models
- Better cosmetic scar outcomes in dermatologic settings
Benefit #4 — Tendon & Ligament Support
Tendons and ligaments are slow-healing structures due to limited blood supply. TB-4 addresses this through both its angiogenic and fibroblast-activating properties.
A 2013 study on medial collateral ligament (MCL) injury in rats showed that TB-4 administration significantly improved ligament healing. Treated ligaments showed more evenly spaced collagen fiber bundles, larger collagen fibril diameters, and significantly better biomechanical properties than controls at 4 weeks (Xu et al., 2013).
TB-4 supports tendon and ligament repair through:
- Fibroblast activation — increased production of structural repair cells
- ECM remodeling — organized collagen deposition rather than disordered scar
- Angiogenesis — new blood vessel formation in the avascular injury zone
- Anti-inflammatory modulation — reduced swelling and inflammatory damage
This makes TB-4 particularly relevant for research into tendinopathy, ligament strain, sports injuries, and overuse conditions. For an in-depth comparison of healing peptides for these applications, see our BPC-157 vs TB-500 comparison.
Benefit #5 — Muscle Recovery & Satellite Cell Activation
TB-4 promotes activation of satellite cells — the resident stem-like cells responsible for muscle repair and regeneration after injury.
A 2010 study by Tokura et al. demonstrated that muscle injury triggers local TB-4 release, which acts as a chemoattractant for myoblasts — the precursor cells that differentiate into new muscle fibers. This chemotactic effect recruits repair cells specifically to the site of damage (Tokura et al., 2010).
A 2021 proteomics study made a striking discovery: TB-4 was the most upregulated secreted protein from contracting muscle cells (C2C12 myotubes) and was acutely increased in the plasma of exercising humans, identifying it as a human "exerkine" — a factor released during exercise that may mediate inter-organ communication (Gonzalez-Franquesa et al., 2021).
A review of muscle-injury research described TB-4 as a chemotactic factor that attracts satellite cell-derived myoblasts and facilitates skeletal muscle regeneration (Hara, 2011).
Benefits include:
- Faster muscle recovery after injury or intense exercise
- Better mechanical resilience in repaired tissue
- Enhanced muscle fiber regeneration through satellite cell recruitment
TB-4 is not a "performance enhancer" in the traditional sense — it's a recovery enhancer that works by accelerating the body's natural repair cascade.
Benefit #6 — Cardiac & Vascular Protection
In cardiac research, TB-4 localizes to areas of heart injury and activates survival pathways. This is the least-known but most biologically impressive TB-4 effect — and the most actively studied area.
Bock-Marquette et al. showed that TB-4 promotes survival of cardiomyocytes after ischemic injury by activating Akt (a key cell-survival kinase) and limiting apoptosis in the infarct zone (Bock-Marquette et al., 2004; Bock-Marquette et al., 2010). A seminal 2007 study demonstrated TB-4 activates epicardial progenitor cells — cells thought to be dormant after embryonic development — enabling cardiac tissue regeneration (Smart et al., 2007).
TB-4 was developed for clinical evaluation in ischemic heart disease based on consistent animal model data showing:
- Fewer dying cardiomyocytes in the infarct and border zones
- Improved heart tissue remodeling post-infarction
- Increased vascular density through angiogenesis in damaged myocardium
- Activation of epicardium-derived progenitor cells for cardiac regeneration
A 2007 review summarized TB-4's cardiovascular significance: it's one of the few peptides that both rescues existing heart cells and promotes formation of new vasculature in the damaged region — a dual mechanism that most cardiac therapies lack (Smart et al., 2007).
Benefit #7 — Skin Repair & Cosmetic Rejuvenation
TB-4's actin-modulating and anti-inflammatory properties make it one of the most studied peptides in dermal wound healing.
Kleinman and Sosne reviewed evidence that TB-4, with its angiogenic and anti-inflammatory activity, increases the rate of dermal healing in preclinical models including diabetic and aged animals, and accelerated repair in phase 2 trials in pressure ulcers, stasis ulcers, and epidermolysis bullosa wounds (Kleinman & Sosne, 2016). An earlier report on two phase 2 trials of stasis and pressure ulcers described healing accelerated by almost a month in the patients who healed (Treadwell et al., 2012).
Earlier work showed TB-4 was also effective in diabetic and elderly wound models — populations where wound healing is critically impaired (Philp et al., 2003).
TB-4's dermal benefits include:
- Collagen organization — organized fibers vs. disordered scar tissue
- Accelerated wound closure — faster re-epithelialization
- Reduced scarring — anti-fibrotic modulation prevents excessive collagen deposition
- Improved elasticity — healthier ECM architecture
- Anti-inflammatory skin calming — reduced redness and irritation
This is why TB-4 is increasingly referenced in regenerative dermatology. For another peptide with complementary skin benefits, see GHK-Cu, a copper peptide known for stimulating collagen synthesis and often stacked with TB-4 for dermal healing protocols.
4. Thymosin Beta-4 vs TB-500

This is one of the most common questions in peptide research. TB-500 is not the same peptide as Thymosin Beta-4, though they are closely related.
What Is TB-500?
TB-500 is a synthetic peptide corresponding to the active region of Thymosin Beta-4 — specifically, the N-terminally acetylated fragment containing amino acids 17–23 (Ac-LKKTETQ). Anti-doping researchers detected this acetylated fragment in a TB-500 product and synthesized it as a reference standard (Esposito et al., 2012). LKKTETQ is TB-4's central actin-binding domain, which a review of TB-4 active sites linked to angiogenesis, wound healing, and cell migration (Sosne et al., 2010).
Key Differences
| Feature |
TB-4 (Thymosin Beta-4) |
TB-500 |
| Structure |
Full 43-amino acid peptide |
Synthetic fragment (7 amino acids) |
| Origin |
Endogenous — naturally produced |
Synthetic — lab-manufactured |
| Stability |
Lower — larger molecule, shorter shelf life |
Higher — smaller, more stable |
| Mechanism |
Full actin sequestration + multi-pathway |
Targeted actin-binding & migration signaling |
| Tissue distribution |
Broad — carried by platelets and immune cells |
Extremely broad — smaller molecule diffuses further |
| Research depth |
Extensive peer-reviewed literature |
Fewer direct studies, most extrapolated from TB-4 |
| Cost |
Higher |
Lower |
Which Is "Better"?
Neither is objectively better — they serve different research contexts:
- TB-4 provides the complete native signaling cascade, including pathways that may not be replicated by the fragment alone (e.g., full progenitor cell activation)
- TB-500 offers enhanced stability and potentially broader tissue distribution due to its smaller size, at a lower cost
Many researchers study them in combination, reasoning that TB-500 provides the core repair signal with superior distribution while TB-4 provides the full biological context.
5. Dosing Overview
For educational and research discussion only. This is not medical advice.
No FDA-approved human dosing exists for TB-4. Published research protocols generally use a loading phase (higher frequency for 2–4 weeks) followed by a maintenance phase (reduced frequency for 4–12+ weeks). Subcutaneous injection is the most common route, with doses typically in the 5–10 mg/week range during loading and 2–5 mg/week for maintenance.
TB-4 has a short plasma half-life (~2 hours IV), which is why research models favor divided dosing and an initial saturation period.
→ Read the complete TB-4 dosing guide with protocols, injection routes & study citations →
6. Stacking Protocols (Research Context)

TB-4 is frequently studied alongside complementary healing peptides whose mechanisms don't overlap with its actin-driven repair pathway:
-
TB-4 + BPC-157 — The most common combination. BPC-157 works through nitric oxide and growth factor pathways; TB-4 through actin mobilization and angiogenesis. Non-overlapping mechanisms suggest synergistic repair. See our TB-4 + BPC-157 stack guide for detailed protocols.
-
TB-4 + GHK-Cu — Copper-dependent collagen synthesis (GHK-Cu) paired with cell migration and vascular support (TB-4). Studied primarily in dermal healing contexts.
-
TB-4 + TB-500 — Full peptide + active fragment for complete signaling cascade with enhanced tissue distribution. See Section 4.
For detailed stacking protocols and dosing, see our peptide stacking guide and TB-4 dosing guide.
7. Safety & Risks
TB-4 is an endogenous peptide, which provides a baseline safety profile different from purely synthetic compounds. However, exogenous administration at supraphysiological levels carries considerations.
Generally Well-Tolerated
The Phase I clinical trial of synthetic TB-4 in healthy volunteers showed:
- No serious adverse events at doses up to 1,260 mg IV
- No clinically significant changes in vital signs, ECG, or laboratory values
- Favorable pharmacokinetic profile (Ruff et al., 2010)
Theoretical Cancer Concern
TB-4 promotes cell migration, angiogenesis, and reduces apoptosis — all processes that could theoretically support tumor growth. Some studies have found elevated TB-4 in certain cancer cell lines.
Important context: Being found in cancer cells does not mean TB-4 causes cancer. TB-4 is found in virtually every cell type. The relationship between exogenous TB-4 and cancer risk has not been established in clinical studies. However, this theoretical concern means TB-4 should be avoided by anyone with active malignancy.
Injection Site Reactions
Common with any subcutaneous peptide:
- Mild redness or irritation at injection site
- Occasional mild swelling
- Generally transient and self-resolving
Limited Long-Term Human Data
While animal studies are extensive, long-term human safety data is limited. The Phase I trial demonstrated short-term safety, but multi-year data is not yet available.
8. Research Evidence Summary
TB-4 has been studied across a remarkably wide range of tissue types and injury models:
| Research Area |
Key Finding |
Source |
| Dermal wounds |
Accelerated re-epithelialization and collagen deposition |
Malinda et al., 1999 |
| Chronic wounds |
Effective in diabetic and elderly wound models |
Philp et al., 2003 |
| Burn wounds |
Rapid vascular remodeling of damaged dermal tissue |
Kim et al., 2015 |
| Ligament injury |
Better biomechanical properties and collagen organization |
Xu et al., 2013 |
| Cardiac ischemia |
Cardiomyocyte survival and vascular regeneration |
Bock-Marquette et al., 2004 |
| Epicardial progenitors |
Progenitor cell activation for cardiac regeneration |
Smart et al., 2007 |
| Muscle injury |
Satellite cell chemoattraction and regeneration |
Tokura et al., 2010 |
| Liver fibrosis |
Reduced oxidative stress and fibrogenic gene expression |
Shah et al., 2018 |
| Lung fibrosis |
Suppressed LPS-induced fibrosis |
Tian et al., 2022 |
| Corneal repair |
Accelerated healing and reduced inflammation |
Sosne et al., 2002 |
| Exercise biology |
Identified as a human exerkine |
Gonzalez-Franquesa et al., 2021 |
| Phase I safety |
No serious adverse events up to 1,260 mg IV |
Ruff et al., 2010 |
The consistency of healing effects across tissues is why TB-4 is often described as the most universal repair peptide. A 2015 review confirmed potential clinical applications spanning kidney disease, liver disease, spinal cord injury, bone repair, and ligament damage (Goldstein, 2015).
9. Frequently Asked Questions
Does TB-4 help healing?
Research models consistently show accelerated wound healing, angiogenesis, and tissue regeneration across dermal, cardiac, muscle, and connective tissue models (Philp & Kleinman, 2010).
Does TB-4 reduce inflammation?
Yes. Studies show TB-4 suppresses TNF-α-induced NF-κB activation and reduces downstream production of IL-6, TNF-α, and fibrosis markers (Qiu et al., 2011). It also modulates inflammation through autophagy pathways (Renga et al., 2018).
Is TB-4 the same as TB-500?
No — TB-500 is a synthetic fragment (amino acids 17–23) of the full 43-amino acid Thymosin Beta-4 peptide. They share the core actin-binding mechanism but differ in size, stability, and biological breadth. See Section 4 for the full comparison.
Does TB-4 affect growth hormone?
No. TB-4 works through actin binding and structural repair pathways — it has no effect on the GH axis, cortisol, or pituitary hormones. This is fundamentally different from peptides like CJC-1295 or Ipamorelin.
Is TB-4 natural?
Yes. TB-4 is endogenous — it's naturally produced in human tissues and found in high concentrations in blood platelets, neutrophils, macrophages, and the thymus gland. It was identified as a human "exerkine" released during exercise (Gonzalez-Franquesa et al., 2021).
Why is it called "beta-4"?
It was the fourth beta-thymosin peptide isolated from thymus gland extracts during research in the 1960s–70s. The "beta" refers to its isoelectric point classification (acidic), distinguishing it from alpha-thymosins like Thymosin Alpha-1.
What is TB-4 used for in research?
TB-4 research spans wound healing, cardiac repair, muscle recovery, tendon healing, corneal injury, and anti-fibrotic applications. Its most actively studied area is cardiac regeneration via epicardial progenitor cell activation.
Where can I learn about TB-4 dosing?
See our dedicated TB-4 Dosing Guide for loading/maintenance protocols, injection routes, and study citations.
10. TB-4 vs Other Healing Peptides
| Peptide |
Primary Mechanism |
What It's Best For |
| TB-4 |
Actin remodeling + angiogenesis |
Tissue repair, wound healing, cardiac models |
| TB-500 |
Active fragment of TB-4 |
Similar repair benefits, smaller molecule, more stable |
| BPC-157 |
Growth factor + NO modulation |
Gut healing, tendon/ligament, systemic anti-inflammatory |
| GHK-Cu |
Copper-dependent collagen synthesis |
Skin rejuvenation, scar remodeling, hair follicles |
| LL-37 |
Antimicrobial + immune modulation |
Infection-related wound healing, immune defense |